Материал: 2016_Kaplan_USMLE_Step_1_Lecture_Notes_Pharmacology

Section IV λ CNS Pharmacology
Clinical Correlate |
|
− GABAA activation ↑ Cl− influx |
||||||
Flumazenil |
|
− GABA |
B |
activation ↑ K+ efflux |
||||
This nonspecific BZ receptor antagonist |
|
− Both mechanisms result in membrane hyperpolarization |
||||||
º |
Benzodiazepines: |
|||||||
is used to reverse the CNS depression |
||||||||
|
|
|
|
|
|
|
||
caused by BZs used in anesthesia or |
|
|
|
Potentiate GABA |
||||
in BZ overdose. Flumazenil cannot |
|
|
|
↑ the frequency of Cl− channel opening |
||||
reverse the CNS depression caused by |
|
|
|
Have no GABA mimetic activity |
||||
barbiturates and alcohols. |
|
|
|
|||||
|
|
|
Act through BZ receptors |
|||||
|
|
|
|
|||||
|
|
|
|
These receptors are part of the GABAA complex |
||||
|
|
|
|
BZ1 mediates sedation |
||||
|
|
|
|
BZ2 mediates antianxiety and impairment of cognitive functions |
||||
|
º |
Barbiturates: |
||||||
|
|
|
|
Prolong GABA activity |
||||
|
|
|
|
↑ duration of Cl− channel opening |
||||
|
|
|
|
Have GABA mimetic activity at high doses |
||||
|
|
|
|
Do not act through BZ receptors |
||||
|
|
|
|
Have their own binding sites on the GABAA complex |
||||
|
|
|
|
Also inhibit complex I of electron transport chain |
||||
|
|
λ Uses of BZs: |
||||||
|
Table IV-1-1. Uses of Various Benzodiazepines |
|||||||
|
|
|
|
|
|
|
|
|
|
|
Drug |
|
|
|
Indications |
|
|
|
|
Alprazolam |
|
Anxiety, panic, phobias |
||||
|
|
Diazepam |
|
|
Anxiety, preop sedation, muscle relaxation, |
|||
|
|
|
|
|
withdrawal states |
|||
|
|
Lorazepam |
|
|
Anxiety, preop sedation, status epilepticus (IV) |
|||
|
|
Midazolam |
|
|
Preop sedation, anesthesia IV |
|||
|
|
Temazepam |
|
Sleep disorders |
||||
|
|
Oxazepam |
|
|
Sleep disorders, anxiety |
|||
λPharmacokinetics of BZs:
−Liver metabolites are also active compounds, except for oxazepam, temazepam, and lorazepam
λUses of barbiturates:
−Phenobarbital is used for seizures
134
Chapter 1 λ Sedative-Hypnotic-Anxiolytic Drugs
λPharmacokinetics of barbiturates:
−Liver metabolized, sometimes to active compounds
−General inducers of cytochrome P450s
−Contraindication in porphyrias
λTolerance to and dependence on sedative-hypnotics:
−Chronic use leads to tolerance
−Cross-tolerance occurs between BZs, barbiturates, and ethanol
−Psychologic and physical dependence occur
−But abuse liability of BZs is < ethanol or barbiturates
−Withdrawal signs of BZs:
ºRebound insomnia
ºAnxiety
ºSeizures when BZs were used as antiepileptic or in high doses
−Withdrawal signs of barbiturates and ethanol:
ºAnxiety
ºAgitation
ºLife-threatening seizures (delirium tremens with alcohol)
−Management of withdrawal: supportive and long-acting BZs
λDrug interactions
−GABAA drugs are:
ºAdditive with other CNS depressants (possible life-threatening
respiratory depression), such as anesthetics, antihistamines, opiates, β-blockers, etc.
ºBarbiturates induce metabolism of most lipid-soluble drugs, such as oral contraceptives, carbamazepine, phenytoin, warfarin, etc.
λNon-BZ drugs:
−Zolpidem and zaleplon
ºBZ1 receptor agonist
ºLess effect on cognitive function (BZ2-mediated)
ºOverdose reversed by flumazenil
ºUsed in sleep disorders
ºLess tolerance and abuse liability (sleepwalking)
−Buspirone
ºNo effect on GABA
º5-HT1A partial agonist
ºUsed for generalized anxiety disorders
ºNonsedative
ºTakes 1 to 2 weeks for effects
135

Section IV λ CNS Pharmacology
Chapter Summary
λSedative-hypnotic-anxiolytic drugs include the benzodiazepines, barbiturates, and alcohols.
λS-H drugs ideally should reduce anxiety without affecting mental or motor function. However, most do affect mental or motor function. Figure IV-1-1 illustrates the relative effects on these functions of classes of S-H drugs at increasing concentrations.
λMost S-H drugs facilitate GABA action by binding to the GABAA receptor, which has one binding site for barbiturates and alcohol and another for benzodiazepines (Figure IV-1-2). The binding of these drugs at these sites leads to increased Cl– influx, potentiating the inhibitory transmitter effects of GABA. The differences in action of the various S-H drugs relate to the differences in the binding site used. Further heterogeneity is introduced by the existence of two subtypes of benzodiazepine receptors, BZ1 and BZ2.
λThe benzodiazepines are used to treat anxiety states and sleep disorders.
Dose-dependent CNS depression does occur but can be reversed by flumazenil. Chronic use can lead to tolerance and dependency with rebound effects upon withdrawal. Table IV-1-1 summarizes the various benzodiazepines and their indications.
λPhenobarbital is used to treat seizures, and thiopental is used as an IV anesthetic. Barbiturates induce deep CNS depression at high doses, and there is no antidote.
λThe barbiturates induce drug-metabolizing enzymes, including the P450 system, leading to potential drug interactions. They also stimulate heme synthesis and are contraindicated in porphyrias.
λTolerance, dependence, and severe withdrawal symptoms are associated with chronic barbiturate use.
λZolpidem and zaleplon are nonbenzodiazepines that bind to the BZ1 receptors and therefore are more specific hypnotics. Buspirone is an anxiolytic that does not work through the GABA system. It is nonsedating and does not cause dependence but takes a week or two to show antianxiety effects.
136

Alcohols 2
Learning Objectives
Answer questions about the mechanism of action and metabolism of alcohol
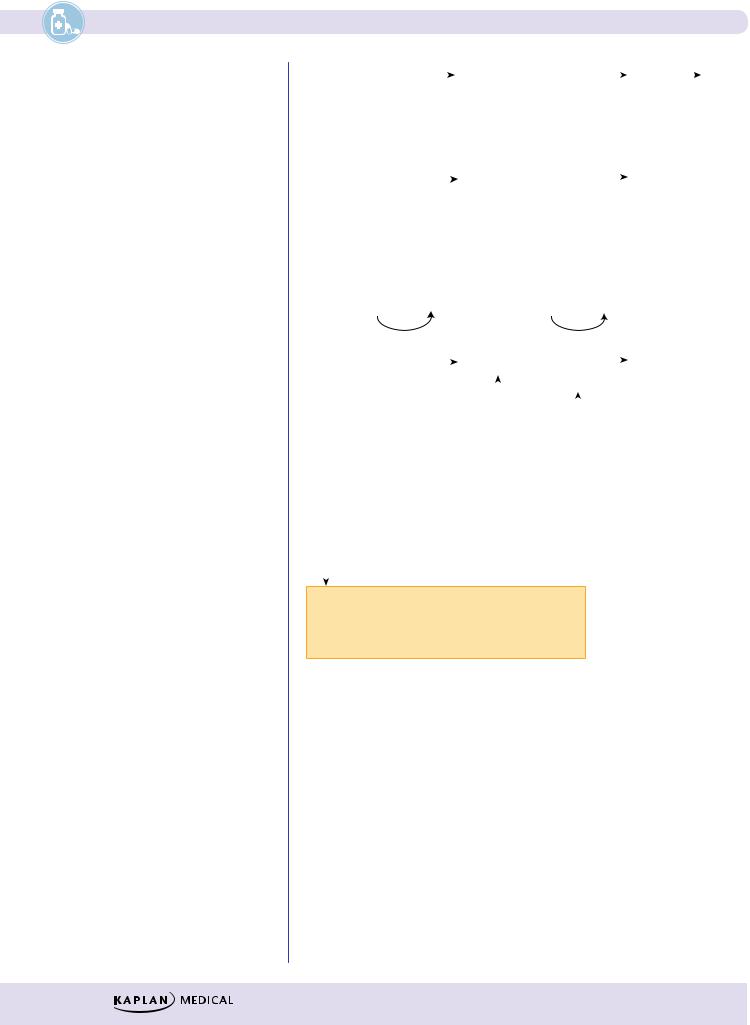
λAll alcohols cause CNS depression, in part through GABA mimetic activity.
λAll alcohols cause metabolic acidosis.
137
Section IV λ CNS Pharmacology
|
|
Ethylene |
|
Alcohol |
|
Glycoaldehyde |
|
|
Aldehyde |
|
Glycolic |
|
|
Oxalic |
||||||||||
|
|
|
glycol |
|
|
|
|
|
|
|
|
|
|
|
acid |
|
|
acid |
||||||
|
|
|
|
dehydrogenase |
|
|
|
dehydrogenase |
|
|
||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
|
|
1. CNS depression |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
|
|
2. Severe metabolic acidosis |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||||
|
|
3. Nephrotoxicity |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
|
|
|
|
|
|
Alcohol |
|
|
|
|
|
|
Aldehyde |
|
|
|
|
|
||||||
|
|
Methanol |
|
|
Formaldehyde |
|
|
Formic acid |
|
|
||||||||||||||
|
|
|
|
|
|
|
dehydrogenase |
|
|
|
||||||||||||||
|
|
|
dehydrogenase |
|
|
|
||||||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
|
|
1. Respiratory failure |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
Clinical Correlate |
2. Severe anion gap metabolic acidosis |
|
|
|
|
|
|
|
|
|
|
|
|
|||||||||||
3. Ocular damage |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||||
Alcohol and Pregnancy |
Treatment for overdose: Fomepizole—long acting inhibitor of alcohol dehydrogenase. |
|||||||||||||||||||||||
Fetal alcohol syndrome is characterized |
High alcohol levels will also require hemodialysis. |
|
|
|
|
|
|
|
|
|||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||
by growth restriction, midfacial |
|
|
|
|
NAD+ |
NADH |
|
|
|
|
NAD+ |
NADH |
|
|
|
|
|
|||||||
hypoplasia, microcephaly, and marked |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
CNS dysfunction, including the frequent |
|
|
|
|
Alcohol |
|
|
|
|
|
|
|
Acetaldehyde |
|
|
|
|
|
||||||
occurrence of mental retardation. |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||||||
Ethanol |
|
|
|
Acetaldehyde |
|
|
Acetic acid |
|
|
|||||||||||||||
|
|
|
dehydrogenase |
|
|
|
||||||||||||||||||
|
|
|
dehydrogenase |
|
|
|
|
|
|
|||||||||||||||
|
|
|
|
|
|
(cytoplasm) |
|
|
|
|
|
|
(mitochondria) |
|
|
|
|
|
||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
In A Nutshell |
1. CNS depression |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||||
2. Metabolic acidosis (ketones) |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||||||||
Drugs that cause disulfiram-like effects: |
3. Acetaldehyde toxicity |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||||||
levels |
|
|
|
|
|
|
|
|
|
|
|
|
|
Inhibited by |
|
|
|
|
|
|
|
|||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||
λ |
Metronidazole |
|
Sociability |
|
|
|
|
|
|
|
|
|
Disulfiram |
|
|
|
|
|
|
|||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||||
|
|
plasma |
|
Gait disturbances |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||||
|
Chlorpropamide |
|
Reaction time |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|||
λ |
|
Ataxia |
|
|
|
|
|
1. N&V |
|
|
|
|
|
|
|
|
|
|
|
|||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
||||||
|
|
|
Impaired motor & mental skills |
2. Headache |
|
|
|
|
|
|
|
|
||||||||||||
λ |
Griseofulvin |
Increasing |
|
Impaired memory |
|
|
3. Hypotension |
|
|
|
|
|
|
|
|
|||||||||
|
|
|
Coma |
|
|
|
|
|
4. Combines with folate to inactivate it |
|
|
|||||||||||||
|
|
|
|
Death |
|
|
|
|
|
5. Combines with thiamine to decrease availability |
||||||||||||||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
Chronic Alcoholism
1.Hypoglycemia
2.Fatty liver and lipemia
3.Muscle wasting (long-term alcoholic, poor food intake)
4.Gout (lactate competes with urate for excretion)
Figure IV-2-1. Metabolism and Pharmacologic Actions of the Alcohols
138