Материал: 2016_Kaplan_USMLE_Step_1_Lecture_Notes_Pharmacology
Section IV λ CNS Pharmacology
DOPAMINE RECEPTORS
–D1-like: Gs coupled
–D2-like: Gi coupled
ºD2A: nigrostriatal
ºD2C: mesolimbic
DRUGS USED IN PARKINSON DISEASE
λSigns and symptoms of Parkinson disease include:
−Bradykinesia
−Muscle rigidity
−Resting tremor
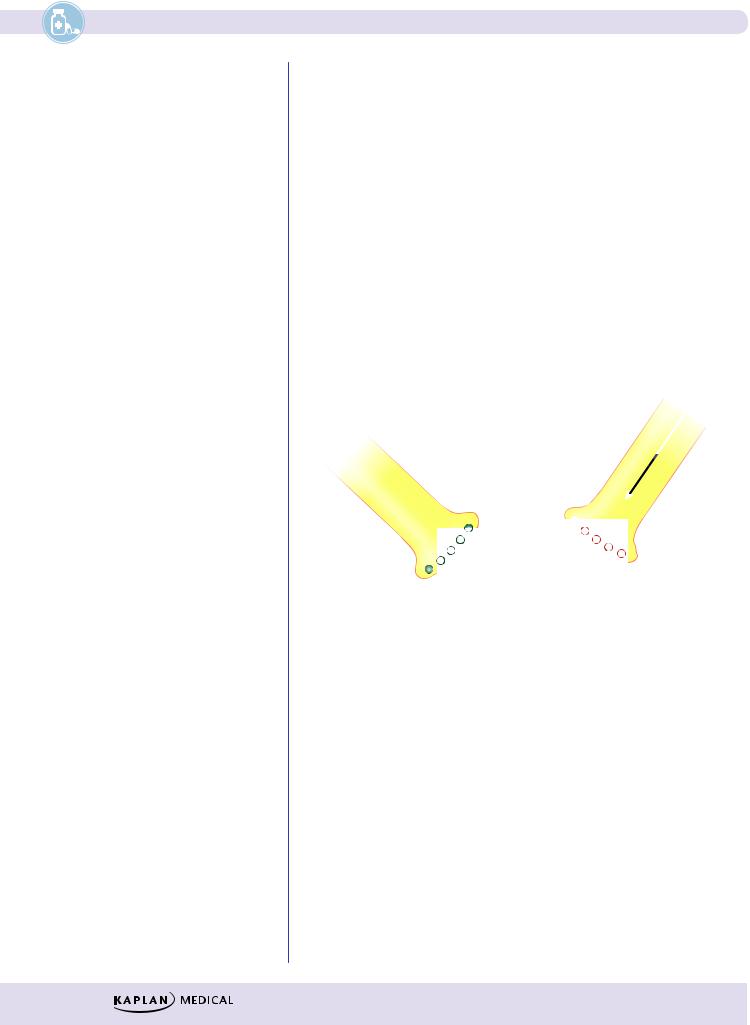
λPathology: degeneration of nigrostriatal dopamine tracts with imbalance between dopamine (↓) and ACh (↑)
Cholinergic
(excitatory)
Dopaminergic
(inhibitory)
|
|
|
|
|
MAO-B |
|
|
|
|
DA |
|
ACh |
|
|
|
|
|
||
L-DOPA increases |
Dopamine |
Muscarinic |
|
|
synthesis of DA |
receptor |
|||
receptor |
||||
|
|
|
||
DA receptor agonists |
|
|
|
|
|
|
|
||
activate |
|
|
|
Selegiline inhibits |
GABA-ergic neuron |
||
M-blockers: |
|
Cholinergic activity |
in striatum |
|
|
||
|
|
||
Figure IV-4-1. CNS Targets for Antiparkinsonian Drugs
λPharmacologic strategy: restore normal dopamine and ↓ ACh activity at muscarinic receptors in the striatum
λDrugs increasing dopamine function:
−Levodopa
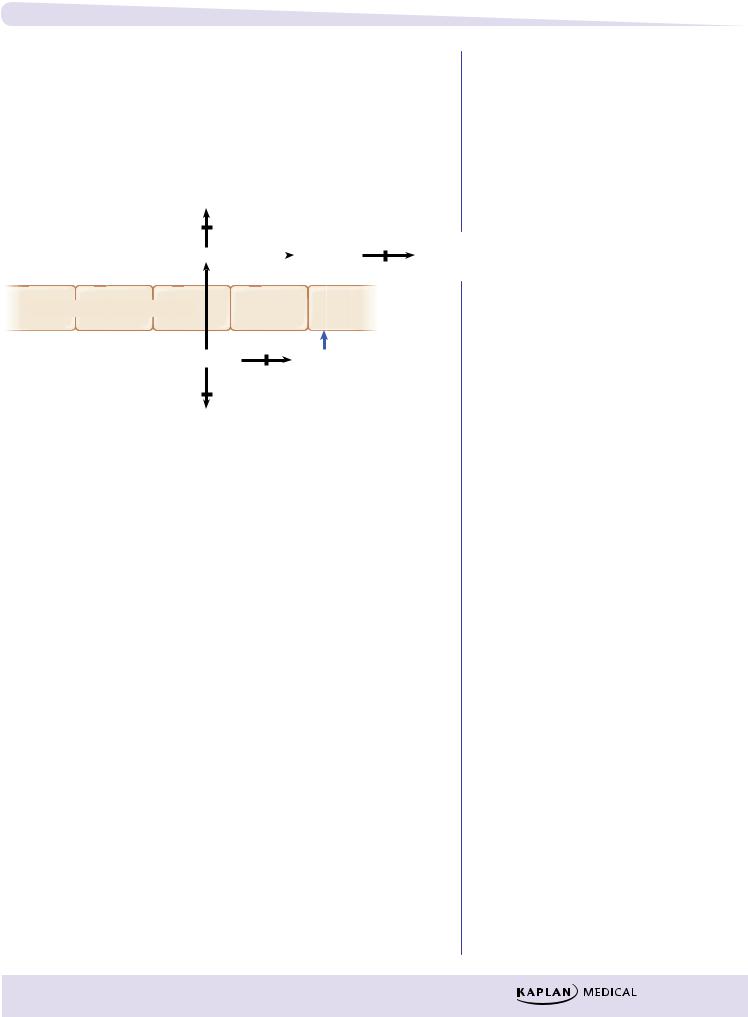
ºProdrug converted to dopamine by aromatic amino acid decarboxylase (AAAD)
ºGiven with carbidopa
144
Chapter 4 λ Drugs Used in Parkinson Disease and Psychosis
º Side effects:
Dyskinesias |
|
|
|
|
|
“On-off” effects |
|
|
|
|
|
Psychosis |
|
|
|
|
|
Hypotension |
|
|
|
|
|
Vomiting |
|
|
|
|
|
3-O-methyldopa |
|
|
|
||
Tolcapone |
COMT |
|
MAOB |
|
|
Levodopa |
AAAD |
Dopamine |
Metabolites |
||
CNS |
|
|
Selegiline |
|
|
Blood–brain barrier (BBB) |
|
|
|
|
|
Periphery |
|
AAAD |
|
|
|
Levodopa |
Dopamine |
|
|
||
COMT |
Carbidopa |
|
|
||
|
|
|
|
|
|
Tolcapone |
|
|
|
|
|
3-O-methyldopa |
|
|
|
|
|
Figure IV-4-2. Inhibitors of Levodopa Metabolism
−Tolcapone and entacapone
ºCOMT converts L-dopa to 3-O-methyldopa, a partial agonist at dopamine receptors.
ºThese drugs inhibit COMT and enhance levodopa uptake and efficacy.
ºTolcapone is hepatotoxic.
−Selegiline
ºMAOB-selective inhibitor (no tyramine interactions)
ºInitial treatment and adjunct to levodopa
ºSide effects: dyskinesias, psychosis, insomnia (metabolized to amphetamine)
λDopamine-receptor agonists:
−Bromocriptine
ºUse: hyperprolactinemia and acromegaly
ºSide effects: dyskinesias and psychosis
−Pramipexole and ropinirole
λDrugs decreasing ACh function:
−Include benztropine and trihexyphenidyl, which are muscarinic blockers
−Actions: ↓ tremor and rigidity but have little effects on bradykinesia
−Side effects: atropine-like
145
Section IV λ CNS Pharmacology
λAmantadine
−Antiviral, which block muscarinic receptors and ↑ dopamine release
−Side effects: atropine-like and livedo reticularis
ANTIPSYCHOTIC DRUGS
Schizophrenia
λPositive symptoms:
−Thought disorders
−Delusions
−Hallucinations
−Paranoia
λNegative symptoms:
−Amotivation
−Social withdrawal
−Flat affect
−Poverty of speech
λ“Dopamine hypothesis”:
−Symptoms arise because of excessive dopaminergic activity in mesolimbic system.
−Dopamine agonists cause psychosis.
−Dopamine antagonists have antipsychotic actions.
λSerotonin is increasingly seen as a part of the etiology of schizophrenia.
λMechanism: blockade of dopamine and/or 5HT2 receptors
λUses
– Schizophrenia
– Schizoaffective states
– Bipolar disorder
– Tourette syndrome and Huntington disease
– Drug or radiation emesis
λSide effects from dopamine blockade:
−Dyskinesias (extrapyramidal symptoms [EPS])
º Acute EPS:
Pseudoparkinsonism, dystonia, akathisia
Management: antimuscarinic drugs (benztropine or diphenhydramine)
º Chronic EPS:
Tardive dyskinesia (TD)
Management: discontinuation/switch to atypical
−Dysphoria
−Endocrine dysfunction:
ºTemperature regulation problems (neuroleptic malignant syndrome [NMS], treated with dantrolene and bromocriptine)
º↑ prolactin (galactorrhea, amenorrhea, gynecomastia)
º↑ eating disorders (weight gain)
146
Chapter 4 λ Drugs Used in Parkinson Disease and Psychosis
λSide effects from muscarinic blockade (particularly tachycardia and ↓ seizure threshold)
λSide effects from alpha blockade (particularly hypotension)
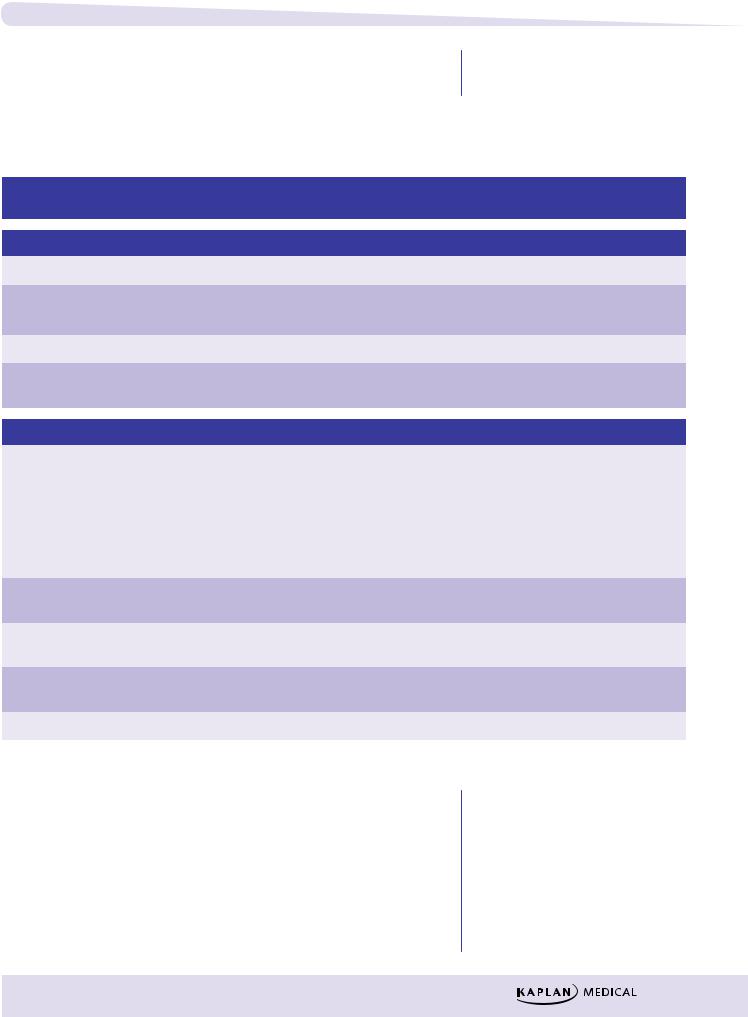
Summary of Antipsychotic Drug Pharmacology
Table IV-4-1. Characteristic Properties of Antipsychotic Drugs
Drug Group |
EPS* |
M Block |
Sedation |
Alpha |
Other |
|
Examples |
|
|
|
Block |
Characteristics |
|
|
|
|
|
|
|
|
Typicals |
|
|
|
|
|
|
Chlorpromazine |
++ |
++ |
+++ |
+++ |
NA |
|
Thioridazine |
+ |
+++ |
+++ |
+++ |
λ |
Cardiotoxicity (torsades—“quinidine-like”) |
|
|
|
|
|
λ |
Retinal deposits |
Fluphenazine |
+++ |
+ |
+ |
+ |
NA |
|
Haloperidol |
+++ |
+ |
+ |
+ |
Most likely cause of neuroleptic malignant |
|
|
|
|
|
|
syndrome (NMS) and TD |
|
|
|
|
|
|
|
|
Atypicals |
|
|
|
|
|
|
Clozapine |
+/– |
++ |
+ |
+++ |
λ Blocks D2c and 5HT2 receptors |
|
|
|
|
|
|
λ |
No TD |
|
|
|
|
|
λ Agranulocytosis—(weekly WBC count) re- |
|
|
|
|
|
|
|
quirement for weekly blood test, weight gain |
|
|
|
|
|
λ Increased salivation (“wet pillow”syndrome) |
|
|
|
|
|
|
λ |
Seizures |
Olanzapine |
+/– |
+ |
+ |
++ |
Blocks 5HT2 receptors, improves negative |
|
|
|
|
|
|
symptoms |
|
Risperidone |
+ |
+/– |
++ |
++ |
Blocks 5HT2 receptors, improves negative |
|
|
|
|
|
|
symptoms |
|
Aripiprazole |
+ |
+/– |
+/– |
+/– |
Partial agonist of D2 receptor; blocks 5HT2 |
|
|
|
|
|
|
receptors |
|
Other atypicals: Quetiapine, Ziprasidone
*Extrapyramidal symptoms
Clinical Correlate
Parenteral Forms
Parenteral formulations of certain antipsychotic drugs (e.g., fluphenazine, haloperidol) are available for rapid initiation of treatment and for maintenance therapy in noncompliant patients. Depot forms of both drugs exist.
147
Section IV λ CNS Pharmacology
Chapter Summary
Dopaminergic Neural Pathways
λDopamine (DA) in the nigrostriatal tract helps regulate kinesis by inhibiting GABA-ergic and cholinergic neurons. The loss of DA neurons in this tract leads to excessive ACh activity and Parkinsonism. DA receptor antagonists cause a reversible pseudo-Parkinsonism; agonists may cause dyskinesis.
λDA neurons in the midbrain projecting into the cerebrocortical and limbic regions regulate affect, reinforcement, psychomotor function, and sensory perception. DA agonists enhance psychomotor activity and reinforcement and at high doses may cause psychoses. DA antagonists decrease psychomotor function.
λIn the hypothalamus, DA released into the pituitary decreases prolactin release. DA agonists (e.g., bromocriptine) are used to treat hyperprolactinemia; antagonists may cause endocrine dysfunction.
λThe activation of DA receptors in the chemoreceptor trigger zone increases emesis; thus, DA agonists are emetic, and antagonists are antiemetic.
Antiparkinsonian Drugs
λParkinsonism is due to an imbalance between DA and ACh activity in the nigrostriatal tract. Drugs attempt to restore this balance either by increasing DA or decreasing ACh levels. Figure IV-4-1 illustrates the CNS sites targeted in antiparkinsonism therapy.
λDrugs used to increase DA function are levodopa, tolcapone, entacapone, bromocriptine, pramipexole, and selegiline. Drugs that decrease ACh function are benztropine, trihexyphenidyl, and amantadine. The properties of each are described.
Antipsychotic Drugs
λAlthough the prevailing concept is that schizophrenia is due to hyperdopaminergic activity in the CNS, not all antischizophrenic drugs act as DA antagonists; some instead modify serotonin function.
λThe typical antipsychotic drugs (e.g., chlorpromazine, thioridazine, fluphenazine, and haloperidol) act primarily as DA antagonists, blocking
D2A receptors. Side effects include the induction of pseudo-Parkinsonism, akathisia, and/or acute dystonic effects. Their use and symptom management are discussed, as are other adverse effects including toxicity, tardive dyskinesia, and neuroleptic malignant syndrome.
λAtypical antipsychotics (e.g., clozapine, risperidone, and olanzapine) act
as antagonists at 5HT2 receptors and seem to have fewer adverse effects.
Aripiprazole is a D2 partial agonist.
λTable IV-4-1 summarizes the characteristics of the antipsychotic drugs.
148