Материал: 2016_Kaplan_USMLE_Step_1_Lecture_Notes_Pharmacology

Section II λ Autonomic Pharmacology
Chapter Summary
λThe autonomic nervous system (ANS) is the major involuntary portion of the nervous system and is responsible for automatic, unconscious bodily functions. It has two major parts: the parasympathetic (PANS) and the sympathetic (SANS) systems.
λGanglia are relay systems set between the CNS and end organs. Ganglia in the SANS system are arranged in a series of parallel nodes adjacent to the vertebral column. In contrast, PANS ganglia are usually located in the innervated organ.
λThe major receptor types are ganglionic nicotinic (NN), endplate nicotinic
(NM), muscarinic (M1–3), and adrenergic receptor of four major subtypes
(α1, α2, β1, β2). ACh is the neurotransmitter at all N receptors, at the
M receptors innervated by postganglionic fibers of the PANS, and the thermoregulatory sweat glands innervated by the SANS. Norepinephrine (NE) is the neurotransmitter at adrenoreceptors innervated by the SANS. NE and epinephrine (E) are released from the adrenal medulla. Dopamine (DA) receptor activation leads to vasodilation in some vascular beds.
λBlood pressure (BP) is a product of the total peripheral resistance (TPR) times the cardiac output (CO). The CO is equal to the heart rate (HR) times the stroke volume (SV). The autonomic (neural) system helps regulate the BP through feedback control involving the baroreceptors, the cardiovascular centers in the brainstem, and the PANS and SANS, which act in an opposing but coordinated manner to regulate the pressure.
λBP is also regulated by hormonal feedback (humoral). Hypotension decreases renal blood flow and activates the release of renin, which leads to the formation of angiotensin II, which in turn stimulates the release of aldosterone from the adrenal cortex. Aldosterone promotes water and salt retention, increasing blood volume and as a consequence increases SV and CO.
44

Cholinergic Pharmacology |
2 |
Learning Objectives
Answer questions about cholinergic neuroeffector junctions
Differentiate between muscarinic receptor activators, receptor antagonists, and nicotinic receptor antagonists
CHOLINERGIC NEUROEFFECTOR JUNCTIONS
|
Choline |
||
Uptake |
+ |
||
Acetyl CoA |
|||
|
|||
Choline |
|
Choline |
|
|
Acetyl |
||
Ca2+ influx |
|
Transferase |
|
ACh |
|||
initiates release |
|
Autoreceptor |
|
|
|
||
Release
Choline
ACh +
AcetylcholineEsterase Acetate
Muscarinic Nicotinic
 Receptors

Effector cells
Figure II-2-1. Cholinergic Neuroeffector Junction
λCholine is accumulated in cholinergic presynaptic nerve endings via an active transport mechanism linked to a Na+ pump and similar to the sodium-dependent glucose transporter.
1Hemicholinium
2Botulinum toxin
3Acetylcholinesterase (AChE) inhibitors
4Receptor agonists and antagonists
45

Section II λ Autonomic Pharmacology
In A Nutshell
λM receptor activation →↓ CV function
λ↑ secretions and ↑ smooth muscle contraction
λAll M receptor activators and blockers are nonspecific.
λCholine uptake is inhibited by hemicholinium ( in Figure II-2-1). ACh is synthesized from choline and acetyl-CoA via choline acetyltransferase (ChAT) and accumulate https://www.annualcreditreport.com s in synaptic vesicles.
λPresynaptic membrane depolarization opens voltage-dependent Ca2+ channels, and the influx of this ion causes fusion of the synaptic vesicle membranes with the presynaptic membrane, leading to exocytosis of ACh. Botulinum toxin ( in Figure II-2-1) interacts with synaptobrevin and other proteins to prevent ACh release and is used in blepharospasm, strabismus/hyperhydrosis, dystonia, and cosmetics.
λSome cholinergic nerve endings have presynaptic autoreceptors for ACh that on activation may elicit a negative feedback of transmitter release.
λInactivation via acetylcholinesterase (AChE) is the major mechanism of termination of postjunctional actions of ACh.
λAChE is a target for inhibitory drugs (indirect-acting cholinomimetics). Note that such drugs can influence cholinergic function only at innervated sites where ACh is released.
λReversible AChE inhibitors ( in Figure II-2-1) include edrophonium, physostigmine, and neostigmine. Irreversible AChE inhibitors include malathion, and parathion.
λPostjunctional receptors (N and M) ( in Figure II-2-1) activated by ACh are major targets for both activating drugs (direct-acting cholinomimetics) and blocking agents.
Table II-2-1. Muscarinic Receptor Activation
Target |
|
|
|
Receptor |
|
|
Response |
Eye |
Sphincter |
|
M3 |
|
Contraction—miosis |
||
|
Ciliary muscle |
|
M3 |
|
Contraction—accommodation for near vision |
||
Heart |
SA node |
|
M2 |
|
↓ Heart rate (HR)—negative chronotropy |
||
|
AV node |
|
M2 |
|
↓ Conduction velocity—negative dromotropy |
||
|
|
|
|
|
|
|
No effects on ventricles, Purkinje system |
Lungs |
Bronchioles |
|
M3 |
|
Contraction—bronchospasm |
||
|
Glands |
|
M3 |
|
Secretion |
||
GI tract |
Stomach |
|
M3 |
|
↑ Motility—cramps |
||
|
Glands |
|
M1 |
|
Secretion |
||
|
Intestine |
|
M3 |
|
Contraction—diarrhea, involuntary defecation |
||
Bladder |
|
|
|
M3 |
|
Contraction (detrusor), relaxation (trigone/sphincter), voiding, |
|
|
|
|
|
|
|
|
urinary incontinence |
Sphincters |
|
|
|
M3 |
|
Relaxation, except lower esophageal, which contracts |
|
Glands |
|
|
|
M3 |
|
Secretion—sweat (thermoregulatory), salivation, and lacrimation |
|
Blood vessels (endothelium) |
|
M3 |
|
Dilation (via NO/endothelium-derived relaxing factor)—no inner- |
|||
|
|
|
|
|
|
|
vation, no effects of indirect agonists |
|
|
|
|
|
|
|
|
46
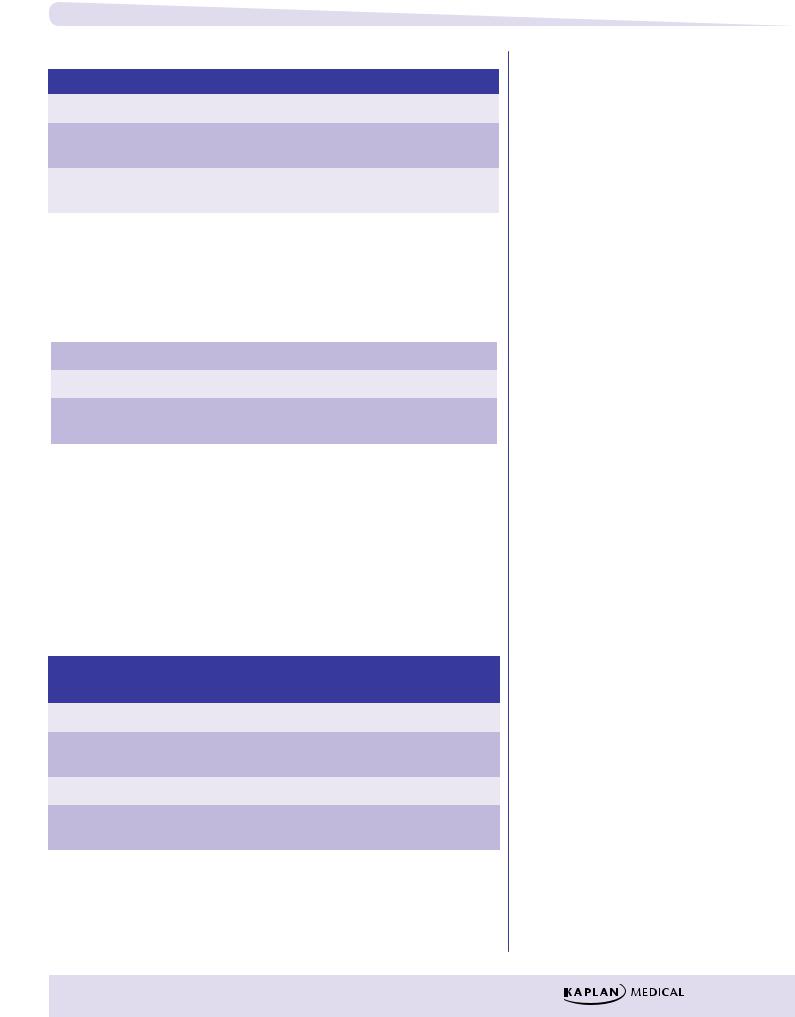
Table II-2-2. Nicotinic Receptor Activation
Target |
|
Receptor |
|
Response |
Adrenal medulla |
|
NN |
|
Secretion of epinephrine and NE |
Autonomic |
|
NN |
|
Stimulation—net effects depend on PANS/ |
ganglia |
|
|
|
SANS innervation and dominance |
Neuromuscular |
|
NM |
|
Stimulation—twitch/hyperactivity of |
junction |
|
|
|
skeletal muscle |
Note: N receptors desensitize very quickly upon exessive stimulation.
Table II-2-3. Cholinergic Receptor Mechanisms
M1 and M3 |
Gq coupled |
↑ phospholipase C →↑ IP3, DAG, Ca2+ |
M2 |
Gi coupled |
↓ adenylyl cyclase →↓ cAMP |
NN and NM |
No 2nd |
activation (opening) of Na/K channels |
|
messengers |
|
MUSCARINICRECEPTOR ACTIVATORS
Muscarinic Agonists
Table II-2-4. Properties of Direct-Acting Cholinomimetics
Drug |
|
Activity |
|
AChE |
|
Clinical Uses |
|
|
|
|
Hydrolysis |
|
|
ACh |
M and N |
+++ |
Short half-life—no clinical use |
|||
Bethanechol |
M |
|
– |
Rx—ileus (postop/neurogenic), |
||
|
|
|
|
|
urinary retention |
|
Methacholine |
M > N |
+ |
Dx—bronchial hyperreactivity |
|||
Pilocarpine, |
M |
|
– |
Rx—xerostomia, |
||
cevimeline |
|
|
|
|
glaucoma (pilocarpine) |
|
Chapter 2 λ Cholinergic Pharmacology
Bridge to Physiology and Anatomy
λBlood vessels are solely innervated by the SANS, so the stimulation
of autonomic ganglia results in vasoconstriction.
λConversely, the gastrointestinal tract is dominated by the PANS, so ganglionic stimulation causes increased gastrointestinal motility and secretions.
47
Section II λ Autonomic Pharmacology
Clinical Correlate
Alzheimer Disease
Late-onset dementia with progressive memory loss and cognitive decline. Neuropathology includes neurofibrillary tangles, amyloid plaques, and loss of ACh neurons in Meynert’s nucleus— rationale for clinical use of AChE inhibitors.
Acetylcholinesterase Inhibitors
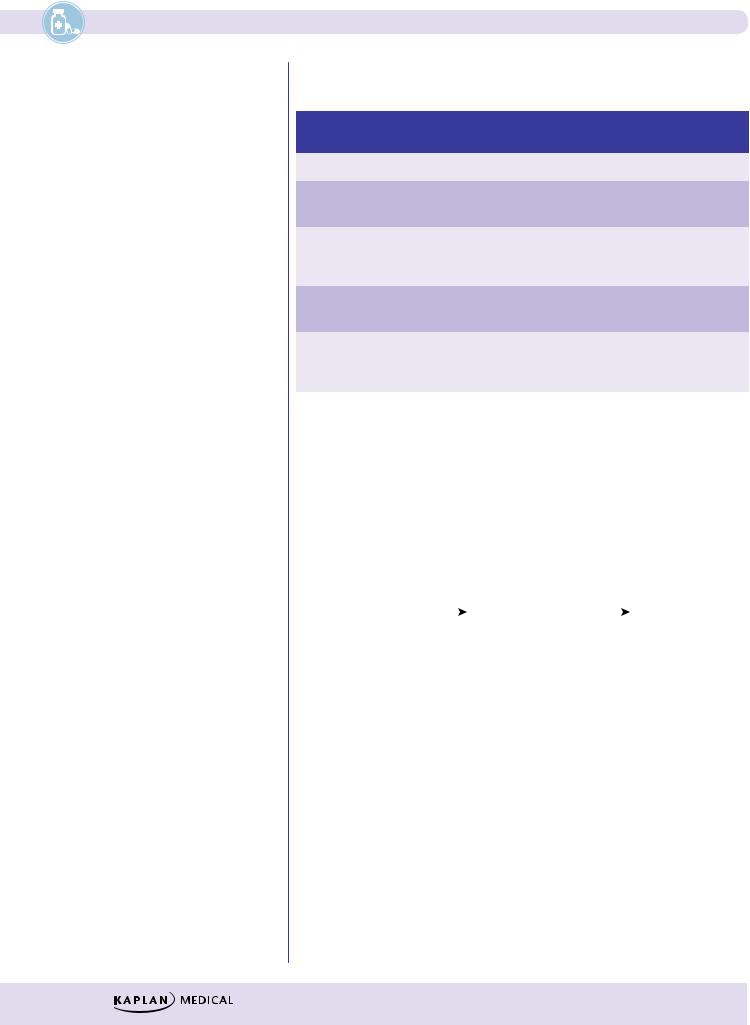
Table II-2-5. Properties of Indirect-Acting Cholinomimetics
Drug |
|
Characteris- |
|
Clinical Uses |
|
|
tics |
|
|
Edrophonium |
Short-acting |
Dx—myasthenia |
||
Physostigmine |
Tertiary amine |
Rx—glaucoma; antidote in atropine |
||
|
(enters CNS) |
overdose |
||
Neostigmine, |
Quaternary |
Rx—ileus, urinary retention, |
||
pyridostigmine |
amines (no |
myasthenia, reversal of |
||
|
CNS entry) |
nondepolarizing NM blockers |
||
Donepezil, |
Lipid-soluble |
Rx—Alzheimer disease |
||
rivastigmine |
(CNS entry) |
|
|
|
Organophosphates |
Lipid-soluble, |
Note: used as insecticides |
||
|
irreversible |
(malathion, parathion) and as nerve |
||
|
inhibitors |
gas (sarin) |
||
Toxicity of AChE Inhibitors
Classic Clue
AChE inhibitor poisoning: “Dumbbeelss”
Diarrhea
Urination
Miosis
Bradycardia
Bronchoconstriction
Emesis
Excitation (CNS/muscle)
Lacrimation
Salivation
Sweating
As insecticides
λLong-acting irreversible inhibitors (both carbamates and organophosphates)
λWide use in agriculture as insecticides
λExamples: malathion and parathion
Inactive |
|
P450 |
Active |
|
P450 |
Inactive |
||
Parathion |
|
Paraoxon |
|
|||||
|
|
|
|
|
|
compounds |
||
Malathion |
|
|
|
Malaoxon |
|
|
|
|
Humans: |
|
Slow |
|
|
Fast |
|
||
Insects: |
|
Fast |
|
|
Slow |
|
||
Figure II-2-2. Activation of Organophosphate Insecticides
Acute toxicity
λExcessive muscarinic and nicotinic stimulations
λMuscarinic effects:
–Diarrhea
–Urination
–Miosis
–Bradycardia
48