Материал: Kaplan USMLE-1 (2013) - Anatomy

Внимание! Если размещение файла нарушает Ваши авторские права, то обязательно сообщите нам

Chapter 3 • Abdomen, Pelvis, and Perineum

Spleen

The spleen is a peritoneal organ in the upper left quadrant that is deep to the left 9th, 10th, and 11th ribs The visceral surface ofthe spleen is in contact with the left colic flexure, stomach, and left kidney. Inasmuch as the spleen lies above the costal margin, a normal-sized spleen is not palpable.

The splenic artery and vein reach the hilus ofthe spleen by traversing the spleno­ renalligament.

Stomach

The stomachhas a right lesser curvature, which is connected to the porta hepatis of the liver by the lesser omentum (hepatogastric ligament), and a left greater curvature from which the greater omentum is suspended (Figure IIl-3-8).

The cardiac region receives the esophagus; and the dome-shaped upper portion ofthe stomach, which is normally filledwithair, is the fundus. The main central part of the stomach is the body. The pyloric portion of the stomach has a thick muscular wall and narrow lumen that empties into the duodenum approximately in the transpyloric plane (Ll vertebra).

Duodenum

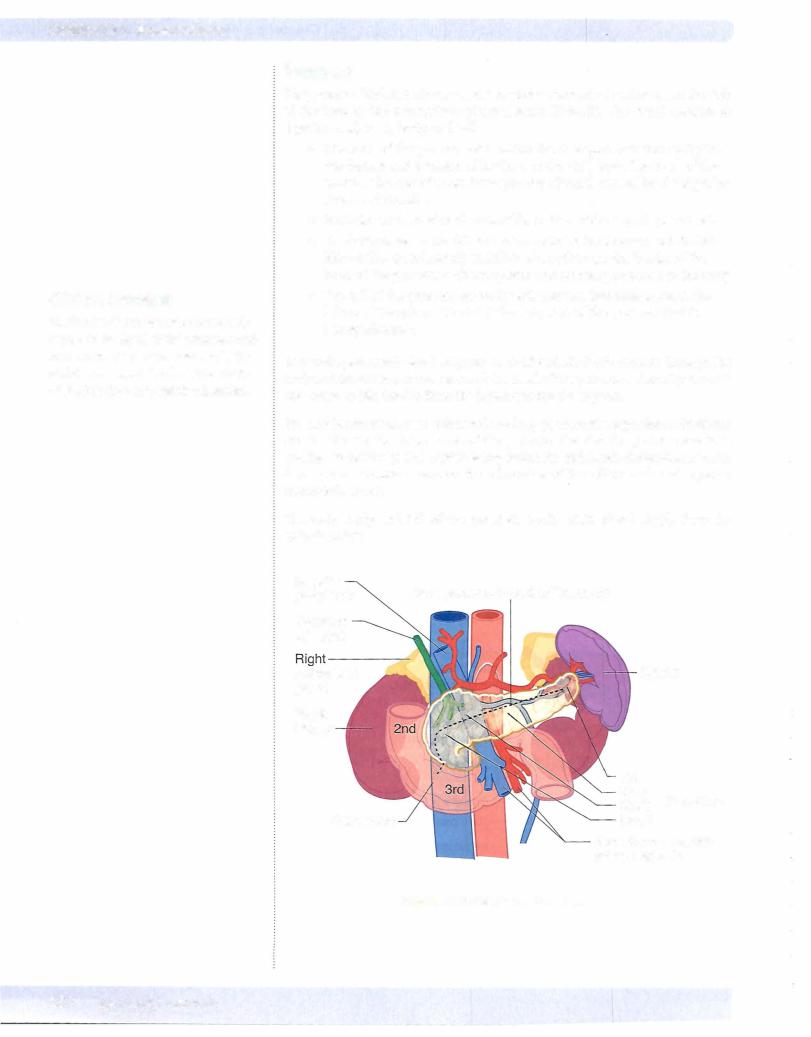
The duodenum is C-shaped, has 4 parts, and is located retroperitoneal except for the first part.

•The first part is referred to as the duodenal cap (bulb). The gastroduode­ nal artery and the common bile duct descend posterior to the first part.

•The second part (descending) receives the common bile duct and main pancreatic duct (Figures III-3-10 and III-3-12) at the hepatopancreatic ampulla (ofVater). Smooth muscle in the wall ofthe duodenal papilla is known as the sphincter of Oddi.

•Note that the foregut terminates at the point of entry of the common bile duct; the remainder ofthe duodenum is part of the midgut.

Jejunum and Ileum

The jejunum begins at the duodenojejunal junction and comprises 2/5 ofthe re­ maining small intestine. The beginning ofthe ileum is not dearly demarcated; it consists ofthe distal 3/5 ofthe small bowel.

The jejunoileum is suspended from the posterior body wall by the mesentery proper. Although the root ofthe mesentery is only 6 inches long, the mobile part ofthe small intestine is approximately 22 feet in length.

Colon

Cecum

The cecum is the firstpart ofthe colon, or large intestine, andbegins at the ileoce­ caljunction. It is a blind pouch, which often has a mesentery and gives rise to the vermiform appendix. The appendixhas its own mesentery, the mesoappendix.

Clinical Correlate

The spleen may be lacerated with a fracture ofthe 9th, 10th, or 11th rib on the left side.

Clinical Correlate

A sliding hiatal hernia occurs when the cardia ofthe stomach herniates through the esophageal hiatus ofthe diaphragm. This can damage the vagal trunks as they pass through the hiatus.

MEDICAL 253

Section Ill • Gross Anatomy

Ascending colon

The ascending colon lies retroperitoneally and lacks a mesentery. It is continuous with the transverse colon at the right (hepatic) flexure of colon.

Transverse colon

The transverse colon has its own mesentery called the transverse mesocolon. It becomes continuous with the descending colon at the left (splenic) flexure of co­ lon. The midgut terminates at the junction of the proximal two-thirds and distal one-third of the transverse colon.

Descending colon

The descending colon lacks a mesentery. It joins the sigmoid colon where the large bowel crosses the pelvic brim.

Sigmoid colon

The sigmoid colon is suspended by the sigmoid mesocolon. It is the terminal portion of the large intestine and enters the pelvis to continue as the rectum.

Rectum

The superior one-third of the rectum is covered by peritoneum anteriorly and laterally. It is the fixed, terminal, straight portion of the hindgut.

Anal Canal

•The anal canal is about 1 .5 inches long and opens distally at the anus. The anal canal is continuous with the rectum at the pelvic diaphragm where it makes a 90-degree posterior bend (anorectal flexure) below the rectum.

•The puborectalis component of the pelvic diaphragm pulls the flexure forward, helping to maintain fecal continence.

•The internal anal sphincter is circular smooth muscle that surrounds the anal canal. The sympathetics (lumbar splanchnics) increase the tone of the muscle and the parasympathetics (pelvic splanchnics) relax the muscle during defecation.

•The external anal sphincter is circular voluntary skeletal muscle sur­ rounding the canal that is voluntarily controlled by the inferior rectal branch of the pudenda!nerve and relaxes during defecation.

•The anal canal is divided in an upper and lower parts separated by the pectinate line, an elevation of the mucous membrane at the distal ends of the anal columns. A comparison of the features of the anal canal above and below the pectinate line is shown in Table III-3-3.

254 MEDICAL

Section Ill • Gross Anatomy

Clinical Correlate

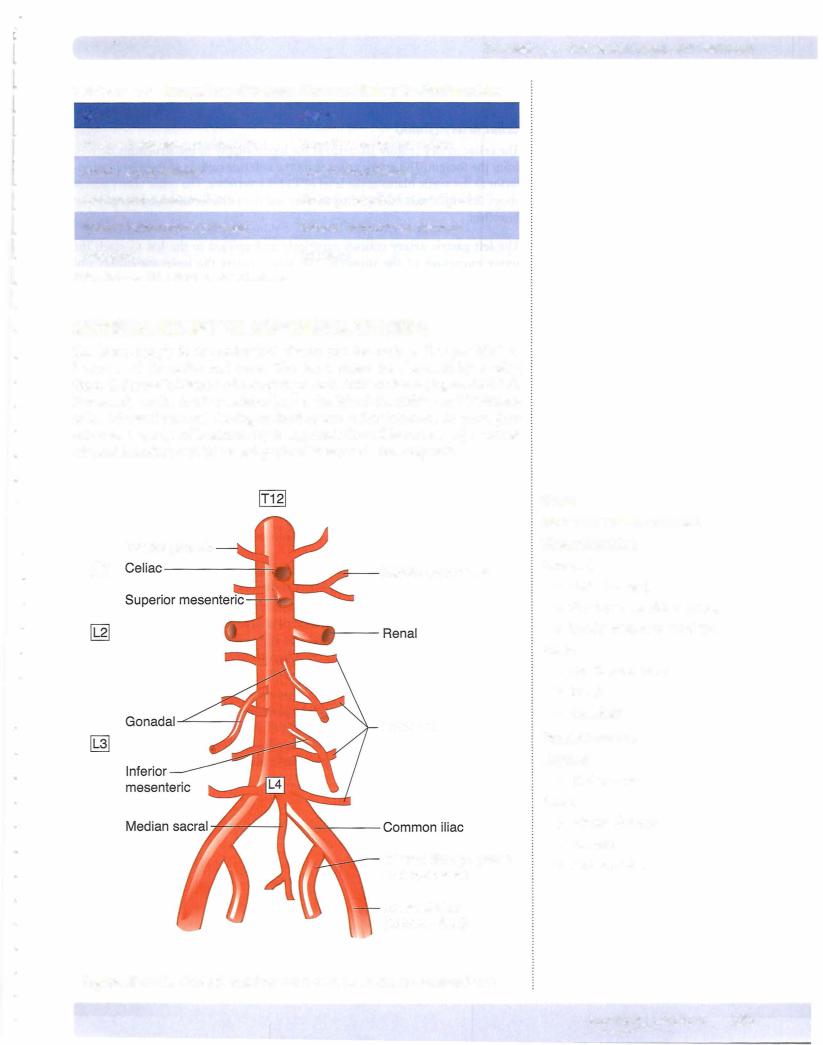
The most common site for an abdominal aneurysm is in the area between the renal arteries and the bifurcation of the abdominal aorta. Signs include decreased circulation to the lower limbs and pain radiating down the back ofthe lower limbs. The most common site of atherosclerotic plaques is at the bifurcation of the abdominal aorta.

Clinical Correlate

•The splenic artery may be subject to erosion by a penetrating ulcer of the posteriorwall of the stomach into the lesser sac.

•The left gastric artery may be subject to erosion by a penetrating ulcer ofthe lesser curvature ofthe stomach.

•The gastroduodenal artery may be subject to erosion by a penetrating ulcer ofthe posterior wall ofthe first part of the duodenum.

Three Unpaired Visceral Arteries

CeliacArtery(Trunk)

The celiac artery (Figure IIl-3- 15) is the blood supply to the structures derived from the foregut. The artery arises from the anterior surface of the aorta just in­ ferior to the aortic hiatus at the level ofT12-Ll vertebra. The celiac artery passes above the superior border of the pancreas and then divides into 3 retroperitoneal branches.

The left gastric artery courses superiorly and upward to the left to reach the lesser curvature of the stomach. The artery enters the lesser omentum and follows the lesser curvature distally to the pylorus. The distribution of the left gastric includes the following:

•Esophageal branch to the distal one inch of the esophagus in the abdo­ men

•Most ofthe lesser curvature

The splenic artery is the longest branch of the celiac trunk and runs a very tortu­ ous course along the superior border of the pancreas. The artery is retroperitone­ al until it reaches the tail of the pancreas, where it enters the splenorenal ligament to enter the hilum of the spleen. The distributions of the splenic artery include:

•Direct branches to the spleen

•Direct branches to the neck, body, and tail ofpancreas

•Left gastroepiploic artery that supplies the left side of the greater cur­ vature of the stomach

•Short gastric branches that supply to the fundus of the stomach

The common hepatic artery passes to the right to reach the superior surface of the first part of the duodenwn, where it divides into its 2 terminal branches:

•Properhepatic artery ascends within the hepatoduodenal ligament of the lesser omentum to reach the porta hepatis, where it divides into the right and left hepatic arteries. The right and left arteries enter the

2 lobes of the liver, with the right hepatic artery first giving rise to the cystic artery to the gallbladder.

•Gastroduodenal artery descends posterior to the first part of the duo­ denum and divides into the right gastroepiploic artery (supplies the pyloric end of the greater curvature of the stomach) and the superior pancreaticoduodenal arteries (supplies the head of the pancreas, where it anastomoses the inferior pancreaticoduodenal branches of the supe­ rior mesenteric artery) .

256 MEDICAL

Источник: https://studfile.net/preview/14638320/