Материал: Oxford American Handbook of Urology ( PDFDrive )
BLADDER CANCER: EPIDEMIOLOGY AND ETIOLOGY 247
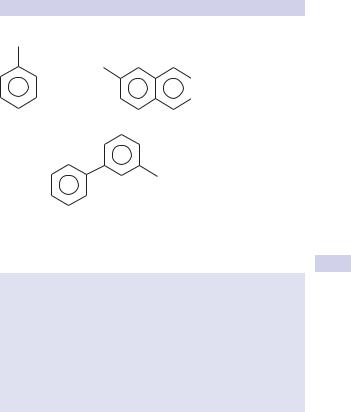
NH2
NH2
aniline |
2-naphthylamine |
NH2
4-aminobiphenyl
Figure 6.5 Carcinogens known to increase risk of bladder cancer.
Box 6.3 Occupations associated with urothelial carcinoma
•Drivers exposed to diesel exhaust
•Dye manufacture
•Fine chemical manufacture (e.g., auramine)
•Hairdressers
•Leather workers
•Painters
•Plumbers
•Rope and textile manufacture
•Rubber manufacture (e.g., tires or electric cable)

248 CHAPTER 6 Urological neoplasia
Bladder cancer: pathology and staging
Benign tumors of the bladder, including inverted papilloma and nephrogenic adenoma, are uncommon. The vast majority of primary bladder cancers are malignant and epithelial in origin:
•>90% are transitional cell carcinoma (TCC); urothelial carcinoma (UC) is now the preferred term.
•1–7% are squamous cell carcinoma (SCC).
•75% are SCC in areas where schistosomiasis is endemic.
•2% are adenocarcinoma
•Rarities include pheochromocytoma, melanoma, lymphoma, and sarcoma arising within the bladder muscle.
•Secondary bladder cancers are mostly metastatic adenocarcinoma from gut, prostate, kidney, or ovary.
Tumor spread
•Direct tumor growth to involve the detrusor, the ureteral orifices, prostate, urethra, uterus, vagina, perivesical fat, bowel, or pelvic side walls.
•Implantation into wounds/percutaneous catheter tracts
• Lymphatic infiltration of the iliac and para-aortic nodes
•Hematogenous, most commonly to liver (38%), lung (36%), adrenal gland (21%), and bone (27%). Any other organ may be involved.
Histological grading
Grading is divided into well, moderately, and poorly differentiated (abbreviated to G1, G2, and G3, respectively).
Staging
Staging is by the TNM (2002) classification (see Fig. 6.6 and Table 6.8). All rely on physical examination and imaging (prefixed c), the pathological classification (prefixed p) corresponding to the TNM categories.
Urothelial carcinoma (transitional cell carcinoma)
UC may be single or multifocal. Because 5% of patients will have a synchronous upper tract UC and metachronous recurrences may develop after several years, the urothelial field-change theory of polyclonality is favored over the theory of tumor monoclonality with implantation (seeding).
Primary UC is considered clinically as superficial or muscle invasive: 70% of tumors are papillary, usually G1 or G2, exhibiting at least 7 transitional cell layers covering a fibrovascular core (normal transitional epithelium has d5 cell layers). Papillary UC is most often superficial, confined to the bladder mucosa (Ta) or submucosa (T1). 10% of patients subsequently develop muscle-invasive or metastatic disease.

BLADDER CANCER: PATHOLOGY AND STAGING 249
T3b |
T3a |
Pelvic |
side |
||
|
|
wall |
|
|
T2 |
|
BLADDER |
T1 |
|
|
|
T4b |
|
|
|
|
Ta |
|
|
Submucosa |
|
|
CIS (red patch) |
|
|
Mucosa (urothelium) |
T4a |
|
Bladder detrusor muscle |
|
|
Prostate |
|
URETHRA |
|
Figure 6.6 Diagrammatic representation of T staging of bladder urothelial cell carcinoma. Reprinted with permission from Brewster S, Cranston D, Noble J, Reynard J (2001) Urology: A Handbook for Medical Students. Informa Healthcare, p. 97.
Table 6.8 2002 TNM staging of bladder carcinoma
Tx |
Primary tumor cannot be assessed |
T0 |
No evidence of primary tumor |
Ta |
Noninvasive papillary carcinoma |
Tis |
Carcinoma in situ |
T1 |
Tumor invades subepithelial connective tissue |
T2 |
Tumor invades muscularis propria (detrusor): T2a inner half; T2b |
|
outer half |
T3 |
Tumor invades beyond muscularis propria into perivesical fat: |
|
T3a = microscopic; T3b = macroscopic (extravesical mass) |
T4a |
Tumor invades any of prostate, uterus, vagina, bowel |
T4b |
Tumor invades pelvic or abdominal wall |
Nx |
Regional (iliac and para-aortic) lymph nodes cannot be assessed |
N0 |
No regional lymph node metastasis |
N1 |
Metastasis in a single lymph node <2 cm in greatest dimension |
N2 |
Metastasis in a single lymph node 2–5 cm or multiple nodes <5 cm |
N3 |
Metastasis in a single lymph node or multiple nodes >5 cm in |
|
greatest dimension |
Mx |
Distant metastasis cannot be assessed |
M0 |
No distant metastasis |
M1 |
Distant metastasis present |
|
|

250 CHAPTER 6 Urological neoplasia
However, a subset of superficial UC, G3T1 tumors, are more aggressive, with 40% subsequently upstaging. 10% of UC have mixed papillary and solid morphology and 10% are solid. These are usually G3, half of which are muscle invasive at presentation.
Ten percent of UC is flat carcinoma in situ (CIS). This is poorly differentiated carcinoma, but confined to the epithelium and associated with an intact basement membrane. Half of CIS lesions occur in isolation; the remainder occur in association with muscle-invasive UC.
CIS usually appears as a flat, red, velvety patch on the bladder mucosa; 15–40% of such lesions are CIS, the remainder being focal cystitis of varying etiology. The cells are poorly cohesive, up to 100% of patients with CIS exhibiting positive urine cytology, in contrast to much lower yields (17–72%) with G1/2 papillary UC.
From 40% to 83% of untreated CIS lesions will progress to muscleinvasive UC, making CIS the most aggressive form of superficial UC. 5% of patients with G1/2 UC and at least 20% with G3 UC (including CIS) have vascular or lymphatic spread.
Metastatic node disease is found in 0% Tis, 6% Ta, 10% T1, 18% T2 and T3a, and 25–33% T3b and T4 UC.
Papillary urothelial neoplasm of low malignant potential (PUNLMP)
The World Health Organization (WHO) defines PUNLMP as a papillary urothelial tumor that resembles an exophytic urothelial papilloma but shows increased cellular proliferation exceeding the thickness of normal urothelium. They are typically small (1–2 cm) and have little, if any, cytological atypia.
Treatment and follow-up are the same as for low-grade noninvasive urothelial carcinoma.
Squamous cell carcinoma (SCC)
SCC is usually solid or ulcerative and muscle invasive at presentation. SCC accounts for only 2–5% of bladder cancers in North America and Europe. SCC in the bladder is associated with chronic inflammation (bladder calculi, indwelling catheters) and urothelial squamous metaplasia, rather than CIS.
Bilharzial SCC is the most common form of bladder cancer in East Africa and the Middle East and is related to infection with Schistosoma hematobium. In Egypt, 80% of SCC cases are induced by the ova of Schistosoma hematobium.
Non-bilharzial SCC is the second-most common form of bladder cancer in North America and Europe. 5% of paraplegics with long-term catheters develop SCC. Smoking is also a risk factor for SCC.
The prognosis is better for bilharzial SCC than for non-bilharzial disease, probably because it tends to be lower grade and metastases are less common in these patients.

BLADDER CANCER: PATHOLOGY AND STAGING 251
Adenocarcinoma
Adenocarcinoma is rare, is usually solid/ulcerative and high grade, and carries a poor prognosis. It is frequently advanced at initial presentation (muscle invasive or metastatic). One-third of cases originate in the urachus, the remnant of the allantois, located deep to the bladder mucosa in the dome of the bladder.
Adenocarcinoma is a long-term (10–20+ year) complication of bladder exstrophy and bowel implantation into the urinary tract, particularly bladder substitutions and ileal conduits after cystectomy. There is association with cystitis glandularis, rather than CIS.
Secondary adenocarcinoma of the bladder may arise as discussed earlier.