Материал: Oxford American Handbook of Urology ( PDFDrive )
This page intentionally left blank

488 CHAPTER 12 Erectile function and ejaculation
Impotence: evaluation
Impotence (also called erectile dysfunction or ED) describes the persistent inability to achieve or maintain a penile erection sufficient for sexual intercourse.
Epidemiology
Moderate to severe ED is found in ~10% of men aged 40–70 years. Prevalence increases with age.
Etiology
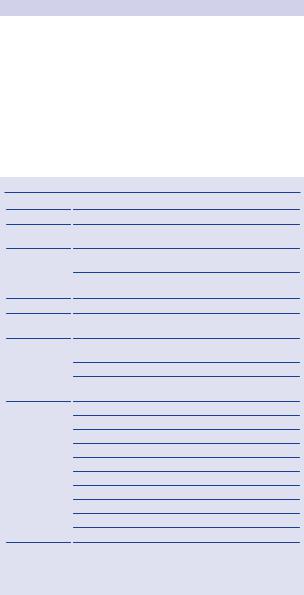
ED is generally divided into psychogenic and organic causes (Table 12.2), although most cases are multifactorial.
History
•Sexual: onset of ED (sudden or gradual); duration of problem; presence of erections (nocturnal, early morning, spontaneous); ability to maintain erections (early collapse, not fully rigid); loss of libido; relationship issues (frequency of intercourse and sexual desire, relationship problems).
•Medical and surgical: hypertension; cardiac disease; peripheral vascular disease; diabetes mellitus; endocrine or neurological disorders; pelvic surgery, radiotherapy, or trauma (damaging innervation and blood supply to the pelvis and penis).
•Drugs: inquire about current medications and ED treatments already tried (and outcome).
•Social: smoking, alcohol consumption.
An organic cause is more likely with gradual onset (unless associated with an obvious cause such as surgery, where onset is acute); loss of spontaneous erections; intact libido and ejaculatory function; existing medical risk factors; and older age groups. The International Index of Erectile Function (IIEF) can be used to quantify severity.
Examination
Full physical examination (CVS, abdomen, neurological); digital rectal examination to assess prostate; external genitalia assessment to document foreskin phimosis and penile lesions (Peyronie’s plaques); confirm presence, size, and location of testicles.
The bulbocavernosus reflex can be performed to test integrity of spinal segments S2–4 (squeezing the glans causes anal sphincter and bulbocavernosal muscle contraction).
Investigation
•Blood tests: fasting glucose; PSA; serum testosterone; sex hormone binding globulin; LH/FSH; prolactin; thyroid function test; fasting lipid profile
•Nocturnal penile tumescence testing: Rigiscan device contains two rings that are placed around the base and distal penile shaft to measure tumescence and number, duration, and rigidity of nocturnal erections. Erections occur most frequently during REM sleep—80%.
IMPOTENCE: EVALUATION 489
•Color Doppler US measures arterial peak systolic and end diastolic velocities,1 preand post-intracavernosal injection of PGE.1
•Cavernosometry: intracavernosal injection of vasoactive drug followed by saline infusion, the rate of which is proportional to the degree of any venous leaking
•Cavernosography: imaging and measurement of blood flow of the penis after intracavernosal injection of contrast and induction of artificial erection. It is used to identify venous leaks.
•Penile arteriography is only indicated in young, otherwise healthy patients with a history of trauma-related impotence in whom vascular reconstruction is being contemplated.
Table 12.2 Causes of erectile dysfunction: “IMPOTENCE”*
Inflammatory |
Prostatitis |
Mechanical |
Peyronie’s disease |
Psychological |
Depression; anxiety; relationship difficulties; lack of |
|
attraction; stress |
Occlusive vascular factors
Arteriogenic: hypertension; smoking; hyperlipidemia; diabetes mellitus; peripheral vascular disease
Venogenic: impairment of veno-occlusive mechanism (due to anatomical or degenerative changes)
Trauma |
Pelvic fracture; spinal cord injury; penile trauma |
|
|
Extra factors |
Iatrogenic: pelvic surgery; prostatectomy |
|
|
|
Other: increasing age; chronic renal failure; cirrhosis |
|
|
Neurogenic |
CNS: multiple sclerosis (MS); Parkinson disease; |
|
|
|
multisystem atrophy; tumor |
|
|
|
Spinal cord: spina bifida; MS; syringomyelia; tumor |
|
|
|
PNS: pelvic surgery or radiotherapy; peripheral |
|
|
|
neuropathy (diabetes, alcohol-related) |
|
|
Chemical |
Antihypertensives (B-blockers, thiazides, ACE inhibitors) |
|
|
|
Antiarrhythmics (amiodarone) |
|
|
|
Antidepressants (tricyclics, MAOIs, SSRIs) |
|
|
|
Anxiolytics (benzodiazepine) |
|
|
|
Antiandrogens (finasteride, cyproterone acetate) |
|
|
|
LHRH analogues |
|
|
|
Anticonvulsants (phenytoin, carbamazepine) |
|
|
|
Anti-Parkinson drugs (levodopa) |
|
|
|
Statins (atorvastatin) |
|
|
|
Alcohol |
|
|
Endocrine |
Hypogonadism; hyperprolactinemia; hypo and |
|
|
|
hyperthyroidism; diabetes mellitus |
|
|
|
|
|
|
* Note that this list of causes of impotence is not in the order of frequency. MAOIs, monoamine-oxidase inhibitors; SSRIs, serotonin reuptake inhibitors.

490 CHAPTER 12 Erectile function and ejaculation
Impotence: treatment
A summary of treatment options is given in Table 12.3.
Psychosexual therapy
The aim is to understand and address underlying psychological issues and provide information and treatment in the form of sex education, instruction on improving partner communication skills, cognitive therapy, and behavioral therapy (programmed relearning of couple’s sexual relationship).
Oral medication
Phosphodiesterase type-5 (PDE5) inhibitors
These include sildenafil (Viagra), tadalafil (Cialis), and vardenafil (Levitra). PDE5 inhibitors enhance cavernosal smooth muscle relaxation and erection by blocking the breakdown of cGMP. Sildenifil and vardenifil crossreact slightly with PDE-6, which may explain visual disturbances; Tadalafil cross-reacts with PDE-11, but the consequences of this are unknown. Sexual stimulus is still required to initiate events.
Side effects include headache, flushing, and visual disturbance. Contraindications are patients taking nitrates; recent myocardial infarc-
tion; recent stroke; hypotension; and unstable angina.
Androgen replacement therapy
Testosterone replacement is indicated for hypogonadism. It is available in oral, intramuscular, pellet, patch, and gel forms. In older men, it is recommended that PSA be checked before and during treatment.
Intraurethral therapy
Alprostadil (MUSE) is used. A synthetic prostaglandin E1 (PGE1) pellet is administered into the urethra via a specialized applicator. Once inserted, the penis is gently rolled to encourage the pellet to dissolve into the urethral mucosa, from where it enters the corpora.
Prostaglandin E1 produces an increase in intracellular cAMP, which leads to decreased calcium concentrations and thus smooth muscle relaxation and increased blood flow to the penis.
Side effects include penile pain, priapism, and local reactions.
Intracavernosal therapy
This involves alprostadil/Caverject™ (synthetic PGE1), and papaverine (smooth muscle relaxant) ± phentolamine (A-adrenoceptor agonist). Training of technique and first dose is given by a health professional. The needle is inserted at right angles into the corpus cavernosum on the lateral aspects of mid-penile shaft.
Adverse effects include pain, priapism, and hematoma.
Vacuum erection device
The device contains three components: a vacuum chamber, pump, and constriction band. The penis is placed in the chamber and the vacuum created by the pump increases blood flow to the corpora cavernosa to

IMPOTENCE: TREATMENT 491
induce an erection. The constriction band is placed onto the base of the penis to retain blood in the corpora and maintain rigidity.
Adverse effects include penile coldness and bruising.
Penile prosthesis
Malleable and inflatable penile prostheses are available for surgical implantation into the corpora to provide penile rigidity sufficient for sexual intercourse.
Side effects include mechanical failure, erosions, and infections.
Table 12.3 Treatment options for erectile dysfunction
Organic |
Psychogenic |
|
|
Eliminate underlying risk factors |
Psychosexual counseling ± partner |
|
|
Oral medication |
Oral medication |
|
|
Androgen replacement |
Intraurethral therapy |
|
|
Intraurethral therapy |
Intracavernosal therapy |
|
|
Intracavernosal therapy |
|
|
|
Vacuum devices |
|
|
|
Penile prosthesis |
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|