Материал: Oxford American Handbook of Urology ( PDFDrive )

URINE EXAMINATION 37
Cloudy urine that is positive for WBCs and is nitrite positive is very likely to be infected.
Urine microscopy
Red blood cell morphology
This is determined by phase-contrast microscopy. RBCs derived from the glomerulus are dysmorphic (they have been distorted by their passage through the glomerulus). RBCs derived from tubular bleeding (tubulointerstitial disease) and those from lower down the urinary tract (i.e., urological bleeding from the renal pelvis, ureters, or bladder) have a normal shape. Glomerular bleeding is suggested by the presence of dysmorphic RBCs, RBC casts, and proteinuria.
Casts
A cast is a protein coagulum (principally, Tamm–Horsfall mucoprotein derived from tubular epithelial cells) formed in the renal tubule and “cast” in the shape of the tubule (i.e., long and thin). The protein matrix traps tubular luminal contents. If the cast contains only mucoproteins it is called a hyaline cast. It is seen after exercise, heat exposure, and in pyelonephritis or chronic renal disease.
RBC casts contain trapped erythrocytes and are diagnostic of glomerular bleeding, most often due to glomerulonephritis. WBC casts are seen in acute glomerulonephritis, acute pyelonephritis, and acute tubulointerstitial nephritis.
Crystals
Specific crystal types may be seen in urine and help diagnose underlying problems (e.g., cystine crystals establish the diagnosis of cystinuria). Calcium oxalate, uric acid, and cystine are precipitated in acidic urine. Crystals precipitated in alkaline urine include calcium phosphate and tri- ple-phosphate (struvite).

38 CHAPTER 2 Urological investigations
Urine cytology
Urine collections for cytology
Exfoliated cells lying in urine that has been in the bladder for several hours (e.g., early morning specimens) or in a urine specimen that has been allowed to stand for several hours are degenerate. Such urine specimens are not suitable for cytological interpretation.
Cytological examination can be performed on bladder washings (using normal saline) obtained from the bladder at cystoscopy (or following catheterization) or from the ureter (via a ureteric catheter or ureteroscope). The urine is centrifuged, and the specimen obtained is fixed in alcohol and stained by the Papanicolaou technique.
Normal urothelial cells are shed into the urine. Under microscopy their nuclei appear regular and monomorphic (diffuse, fine chromatin pattern, single nucleolus).
Causes of a positive cytology report (i.e., abnormal urothelial cells seen—high nuclear–cytoplasmic ratio, hyperchromatic nuclei, prominent nucleoli) include the following:
•Urothelial malignancy (transitional cell carcinoma [TCC], squamous cell carcinoma, adenocarcinoma)
•Previous radiotherapy (especially if within the last 12 months)
•Previous cytotoxic drug treatment (especially if within the last 12 months; e.g., cyclophosphamide, busulphan, cysclosporin)
•Urinary tract stones
Renal adenocarcinoma (clear cell cancer of the kidney) usually does not exfoliate abnormal cells, though occasionally clusters of clear cells may be seen, suggesting the diagnosis.
High-grade urothelial cancer and carcinoma in situ exfoliate cells that look very abnormal, and usually the cytologist is able to indicate that there is a high likelihood of a malignancy. Low-grade bladder TCC exfoliates cells that look very much like normal urothelial cells. The difficulty arises where the cells look abnormal, but not that abnormal—here the likelihood that the cause of the abnormal cytology is a benign process is greater.
Sensitivity and specificity of positive urine cytology for detecting TCC of the bladder depend on the definition of positive—if only obviously malignant or highly suspicious samples are considered positive, then the specificity will be high. Urine cytology may be negative in as many as 20% of high-grade cancers.
If “atypical cells” are included in the definition of abnormal, the specificity of urine cytology for diagnosing urothelial cancer will be relatively poor (relatively high number of false positives) because many cases will have a benign cause (stones, inflammation).

PROSTATIC SPECIFIC ANTIGEN (PSA) 39
Prostatic specific antigen (PSA)
PSA is a 34KD glycoprotein enzyme produced by the columnar acinar and ductal prostatic epithelial cells. It is a member of the human kallikrein family and its function is to liquefy the ejaculate, enabling fertilization. PSA is present in both benign and malignant cells, although the expression of PSA tends to be reduced in malignant cells and may be absent in poorly differentiated tumors. Large amounts are secreted into the semen, and small quantities are found in the urine and blood.
The function of serum PSA is unclear, although it is known to liberate the insulin-like growth factor type 1 (IGF-1) from one of its binding proteins. 75% of circulating PSA is bound to plasma proteins (complexed PSA) and metabolized in the liver, while 25% is free and excreted in the urine. Complexed PSA is stable, bound to A1-antichymotrypsin and A2- macroglobulin. Free PSA is unstable, recently found to consist of two isoforms: pro-PSA is a peripheral zone precursor, apparently elevated in the presence of prostate cancer, and BPSA is the transition zone precursor and associated with benign prostatic hyperplasia (BPH).
The half-life of serum PSA is 2.2 days. A prostate biopsy is often recommended for men with a PSA > 2.5 ng/mL, though this varies with age. Table 2.1 shows a published age-specific normal range (95th percentile).
In the absence of prostate cancer, serum PSA concentrations also vary physiologically, according to race and prostate volume.
Indications for checking serum PSA
•Patient request, following counseling
•Lower urinary tract symptoms
•Abnormal digital rectal examination
•Progressive bone pain, especially back pain
•Unexplained anemia, anorexia, or weight loss
•Spontaneous thromboembolism or unilateral leg swelling
•Monitoring of prostate cancer patients
Table 2.1 Age-adjusted normal range for PSA
Age range (years) |
Normal PSA range (ng/mL) |
40–49 |
<2.5 |
50–59 |
<3.5 |
60–69 |
<4.5 |
>70 |
<6.5 |
|
|

40 CHAPTER 2 Urological investigations
Radiological imaging of the urinary tract
Ultrasound
Ultrasound is a noninvasive method of urinary tract imaging. While it provides good images of the kidneys and bladder, anatomical detail of the ureter is poor and the mid-ureter cannot be imaged at all by ultrasound because of overlying bowel gas.
Uses of ultrasound
Renal
•Assessment of hematuria
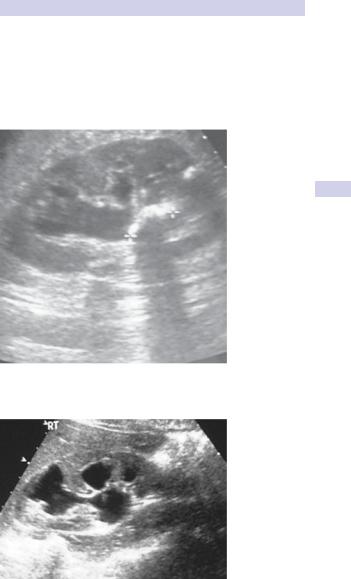
•Determination of nature of renal masses—can differentiate simple cysts (smooth, well-demarcated wall, reflecting no echoes; benign) from solid masses (almost always malignant; cystic masses with solid components or multiple septae or calcification may be malignant) and from those casting an “acoustic shadow” (stones) (Fig. 2.1)
•Can determine the presence or absence of hydronephrosis (dilatation of the collecting system) in patients with abnormal renal function (Fig. 2.2)
•Allows ultrasound-guided nephrostomy insertion in patients with hydronephrosis and renal impairment or with infected, obstructed kidneys
Bladder
•Measurement of post-void residual urine volume
•Allows ultrasound-guided placement of a suprapubic catheter
Prostate: transrectal ultrasound (TRUS)
•Measurement of prostate size (where gross prostatic enlargement is suspected on the basis of a DRE, and surgery, in the form of open prostatectomy, is contemplated)
•To assist prostate biopsy (allows biopsy of hypoechoic or hyperechoic lesions)
•Investigation of azoospermia (can establish the presence of ejaculatory duct obstruction)
Urethra
•Can image the urethra and establish the depth and extent of spongiofibrosis in urethral stricture disease
Testes
•Assessment of the patient complaining of a lump in the testicle (or scrotum)—can differentiate benign lesions (hydrocele, epididymal cyst) from malignant testicular tumors (solid, echo poor or with abnormal echo pattern)
•When combined with power Doppler can establish the presence or absence of testicular blood flow in suspected torsion
•Assessment of testicular trauma (rupture is indicated by abnormal echo pattern, due to blood within the body of the testis; surrounding
RADIOLOGICAL IMAGING OF THE URINARY TRACT 41
hematoma may be seen—blood within the scrotal soft tissues that has escaped through a tear in the tunica albuginea and the visceral and parietal layers of the tunica vaginalis; hematocele—blood contained by an intact parietal layer of the tunica vaginalis)
•Investigation of infertility—varicoceles and testicular atrophy may be identified
Figure 2.1 An acoustic shadow cast by a stone within the kidney.
Figure 2.2 Hydronephrosis. Urine in dilated calyces appears black (hypoechoic).