Материал: Oxford American Handbook of Urology ( PDFDrive )
HYDRONEPHROSIS 407
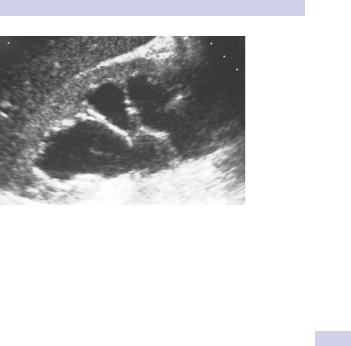
Figure 9.1 Hydronephrosis as seen on renal ultrasonography.
Examination
•Measure blood pressure—elevated in high-pressure chronic retention (HPCR) due to benign prostatic obstruction (caused by fluid overload).
•Bilateral edema (due to fluid overload)
•Abdominal examination—percuss and palpate for an enlarged bladder.
•In men, DRE (?prostate or rectal cancer), and in women, vaginal examination (?cervical cancer)
•Check serum creatinine to determine the functional effect of the hydronephrosis.
•Renal ultrasonography (if not already done)
IVP findings in renal obstruction
•An obstructive (dense) nephrogram
•A delay in filling of the collecting system with contrast material
•Dilatation of the collecting system
•An increase in renal size
•Rupture of fornices (junction between renal papilla and its calyx) with urinary extravasation
•Ureteric dilatation and tortuosity
•A standing column of contrast material in the ureter
Unilateral hydronephrosis
Obtain a KUB X-ray (a ureteric stone may be seen), or CTU (or IVP) if a stone is suspected.
•If no stone is seen, but hydronephrosis is confirmed and ureter is nondilated, the obstruction must be at the UPJ. In the absence of a ureteric stone visible on CTU, the diagnosis must be UPJ obstruction.
•If no stone is seen and the ureter is dilated as well as kidney, ureteric TCC is likely. Arrange for retrograde pyelography to identify site of obstruction, and ureteroscopy/ureteric biopsy.

408 CHAPTER 9 Upper tract obstruction
Bilateral hydronephrosis
•If the patient is in retention or has a substantial post-void residual urine volume, pass a catheter. If the elevated creatinine falls (and the hydronephrosis improves), the diagnosis is bladder outlet obstruction (BOO), due, for example, to BPH, prostate cancer, urethral stricture, or detrusor-sphincter dyssynergia. If the creatinine remains elevated, the obstruction affecting both ureters is higher upstream.
•Obtain TRUS and prostatic biopsy if prostate cancer is suspected on DRE, and a CT scan to look for malignant bilateral ureteric obstruction or abdominal aortic aneurism (AAA).

HYDRONEPHROSIS 409
Box 9.1 Causes of hydronephrosis
Unilateral
•Obstructing ureteric stone
•UPJ obstruction
•Obstructing clot in ureter
•Obstructing ureteric TCC
•Any of the causes listed below when the pathological process has not yet extended to involve both ureters
Bilateral
•Bladder outlet obstruction (BOO)
•BPH
•Prostate cancer
•Urethral stricture
•Detrusor-sphincter dyssynergia (DSD)
•Posterior urethral valve
•Bilateral ureteric obstruction at their level of entry into the bladder
•Locally advanced cervical cancer
•Locally advanced prostate cancer
•Locally advanced rectal cancer
•Poor bladder compliance (often combined with DSD): neuropathic bladder (spinal cord injury, spina bifida); post-pelvic radiotherapy
•Periureteric inflammation
•From adjacent bowel involved with inflammatory bowel disease (e.g., Crohn’s, ulcerative colitis) or diverticular disease
•Retroperitoneal fibrosis
•Idiopathic (diagnosed following exclusion of other causes)
•Periarteritis—aortic aneurysm, iliac artery aneurysm
•Post-irradiation
•Drugs—methysergide, hydralazine, haloperidol, LSD, methyldopa, B-blockers, phenacetin, amphetamines
•Malignant—retroperitoneal malignancy (lymphoma, metastatic disease from e.g., breast cancer), post-chemotherapy
•Chemicals—talcum powder
•Infection—TB, syphilis, gonorrhea, chronic UTI
•Sarcoidosis
•Bilateral UPJ obstruction (uncommon)
•Hydronephrosis of pregnancy (partly due to smooth-muscle relaxant effect of progesterone, partly obstruction of ureters by fetus)
•Hydronephrosis in association with an ileal conduit (a substantial proportion of patients with ileal conduit urinary diversion have bilateral hydronephrosis, in the absence of obstruction)
•Bilateral ureteric stones (rare)

410 CHAPTER 9 Upper tract obstruction
Management of ureteric strictures (other than UPJ obstruction)
Definition
A normal ureter undergoes peristalsis and therefore at any one moment at least one area of the ureter will be physiologically narrowed. A ureteric stricture is a segment of ureter that is narrowed and remains so on several images (i.e., it is a length of ureter that is constantly narrow).
Causes
Most ureteric strictures are benign and iatrogenic. Some follow impaction of a ureteric stone for a prolonged period. Malignant strictures are within the wall of the ureter (e.g., TCC ureter) or due to extrinsic compression from the outside wall of the ureter (e.g., lymphoma, malignant retroperitoneal lymphadenopathy). Retroperitoneal fibrosis (RPF) may be benign (idiopathic, aortic aneurysm, post-irradiation, analgesic abuse) or malignant (retroperitoneal malignancy, post-chemotherapy).
Mechanism of iatrogenic ureteric stricture formation
Normally it is ischemic:
•Usually injury at time of open or endoscopic surgery (e.g., damage to ureteric blood supply or direct damage to ureter at time of colorectal resection, AAA graft, hysterectomy); at ureteroscopy— mucosal trauma (from ureteroscope or electrohydraulic lithotripsy), perforation of ureter (urine extravasation leading to fibrosis)
•Radiotherapy in the vicinity of the ureter
•Stricture of ureteroneocystostomy of renal transplant
Investigations
The stricture may be diagnosed following investigation for symptoms (flank pain, upper tract infection) or may be an incidental finding on an investigation done for some other reason. The stricture may be diagnosed on a renal ultrasound (hydronephrosis), an IVP, or a CTU.
A MAG3 renogram will confirm the presence of obstruction (some minor strictures may cause no renal obstruction) and establish split renal function. Where ureteric TCC is possible, proceed with ureteroscopy and biopsy.
Treatment options
•Nothing (symptomless stricture in an older patient with significant comorbidity or <25% function in an otherwise healthy patient with a normally functioning contralateral kidney)
•Permanent JJ stent or nephrostomy, changed at regular intervals (symptomatic stricture in an older patient with significant comorbidity or <25% function in affected kidney with compromised overall renal function)
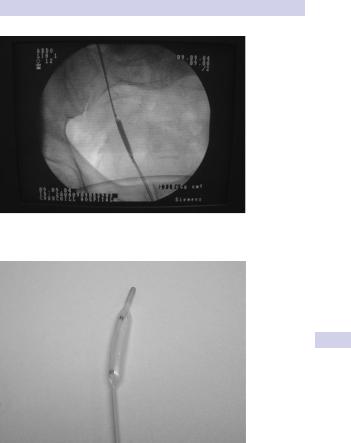
•Dilatation (balloon or graduated dilator) (see Figs. 9.2 and 9.3).
MANAGEMENTOFURETERICSTRICTURES(OTHERTHANUPJOBSTRUCTION)ICTURES 411
Figure 9.2 Balloon dilatation of a lower ureteric stricture.
Figure 9.3 The catheter used for balloon dilatation.