Материал: Oxford American Handbook of Urology ( PDFDrive )
302 CHAPTER 6 Urological neoplasia
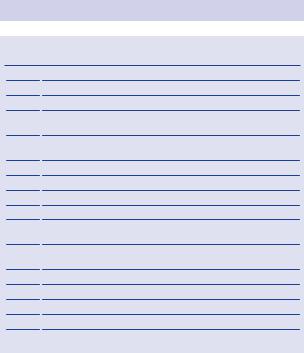
Table 6.16 TNM staging of testicular germ cell tumors. S staging is presented on p. 305
|
|
Tx |
The primary tumor has not been assessed (no radical orchiectomy) |
|
|
T0 |
No evidence of primary tumor |
|
|
Tis |
Intratubular germ cell neoplasia (carcinoma in situ) |
|
|
T1 |
Tumor limited to testis and epididymis without vascular invasion; |
|
|
|
may invade tunica albuginea but not tunica vaginalis |
|
|
T2 |
Tumor limited to testis and epididymis with vascular/lymphatic |
|
|
|
invasion, or tumor involving tunica vaginalis |
|
|
T3 |
Tumor invades spermatic cord with or without vascular invasion |
|
|
T4 |
Tumor invades scrotum with or without vascular invasion |
|
|
Nx |
Regional lymph nodes cannot be assessed |
|
|
N0 |
No regional lymph node metastasis |
|
|
N1 |
Metastasis with a lymph node d2 cm or multiple lymph nodes, |
|
|
|
none >2 cm |
|
|
N2 |
Metastasis with a lymph node size 2–5 cm or multiple lymph nodes, |
|
|
|
collected size 2–5 cm |
|
|
N3 |
Metastasis with a lymph node mass >5 cm |
|
|
Mx |
Distant metastasis cannot be assessed |
|
|
M0 |
No distant metastasis |
|
|
M1a |
Nonregional lymph node or pulmonary metastasis |
|
|
M1b |
Distant metastasis other than to nonregional lymph node or lungs |
|
|
|
|
TESTICULAR CANCER 303
Testicular cancer: prognostic staging system for metastatic germ cell cancer
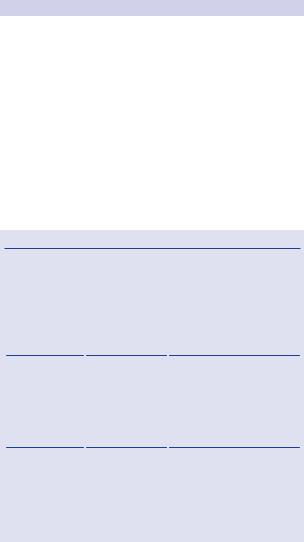
The International Germ Cell Cancer Collaborative Group (IGCCCG) has devised a prognostic factor–based staging system for metastatic germ cell cancer that includes goodand intermediate-prognosis seminoma and good-, intermediate-, and poor-prognosis non-seminomatous germ cell tumors (NSGCT) (Table 6.17).
See p. 299 for discussion on testicular tumor markers, including S staging (p. 305). Primary therapy of testicular cancer is based on the following:
•Histology (seminoma vs. NSGCT)
•Clinical TNM stage.
•International Germ Cell Cancer Collaborative Group (IGCCCG) classification (good, intermediate, or poor risk)
Table 6.17 IGCCCG staging system for metastatic germ cell cancer
|
Seminoma |
NSGCT |
|
|
|
|
|||
Good |
90% of patients |
56% of patients |
|
|
|
||||
5-year progression- |
86% |
92% |
|
|
free survival |
|
Testis or retroperitoneal primary |
|
|
All factors listed |
Any primary site; |
|
||
present: |
no nonpulmonary |
site; no nonpulmonary visceral |
|
|
|
visceral metastases; |
metastases; AFP <1000 ng/mL; |
|
|
|
normal AFP; any |
hCG <5000 mIU/L; and LDH <1.5 |
|
|
|
hCG or LDH |
normal upper limit (S1) |
|
|
Intermediate |
10% of patients |
28% of patients |
|
|
5-year progression- |
73% |
80% |
|
|
free survival |
|
Testis or retroperitoneal primary |
|
|
All factors listed |
Any primary site; |
|
||
present: |
nonpulmonary |
site; no nonpulmonary visceral |
|
|
|
visceral metastases |
metastases; AFP 1000–9999 ng/mL |
|
|
|
present; normal AFP; |
or hCG 5000–49999 mIU/mL; LDH |
|
|
|
Any hCG or LDH |
1.5–10 normal upper limit (S2) |
|
|
Poor |
|
16% of patients |
|
|
5-year progression- |
No patients classified |
48% |
|
|
free survival |
as poor prognosis |
|
|
|
All factors listed |
|
Mediastinal primary; nonpulmonary |
|
|
present: |
|
visceral metastases present; AFP |
|
|
|
|
>10,000 ng/mL or hCG >50,000 |
|
|
|
|
mIU/L; LDH >10 normal upper |
|
|
|
|
limit (S3) |
|
|
|
|
|
|
|

304 CHAPTER 6 Urological neoplasia
Testicular cancer: management of non-seminomatous germ cell tumors (NSGCT)
Following radical orchiectomy and formal staging, the patient may require a retroperitoneal lymph node dissection (RPLND). Joint management involves urology and medical oncology in most cases of NSCGT.
In the presence of elevated AFP, a seminoma would be managed as for teratoma. Combination chemotherapy, introduced in the 1980s, revolutionized the treatment of metastatic testicular teratoma, which was hitherto virtually untreatable.
The IGCCCG prognostic staging is often used in treatment planning at some centers. General treatment options following radical orchiectomy and staging for NSCGT are outlined here (see Table 6.18 for stage grouping).
Stage I
•Surveillance is appropriate for reliable patients with no risk factors. It has a 25–30% relapse rate.
•Requires close follow-up with imaging (CT, CXR), tumor markers, and physical examination
•RPLND: modified unilateral template/nerve-sparing. Up to 70–75% will be pathologically negative (pN0).
•RPLND offers cure in 95% with negative nodes and may cure lowvolume nodal disease. Only 5% will relapse.
•Chemotherapy with two cycles of bleomycin, etoposide, cisplatin (BEP) yields 95% survival.
Stage IIa/IIb
Controversy exists regarding the most effective treatment regimen. Options include RPNLD with modified bilateral template, RPNLD + adjuvant chemotherapy, or primary chemotherapy.
•RPNLD and no tumor found: observe
•RPNLD and positive nodes: two cycles of adjuvant chemotherapy
•RPNLD and high-volume disease or residual tumor left behind: three cycles adjuvant chemotherapy
Stage IIC or III
•Chemotherapy is the initial treatment, with either 3 or 4 cycles depending on risk. Complete responses are frequently observed.
•Partial responses with residual retroperitoneal masses undergo full bilateral RPNLD (nerve-sparing, if applicable). Follow-up is based on pathological findings:
•Residual masses: fibrosis in 40%, teratoma in 40%, and viable malignancy in 20%
•Malignancy present and post-resection tumor markers elevated or tumor left behind: use salvage chemotherapy
•Malignancy present and post-resection tumor markers normal and no tumor left behind: 2 cycles of chemotherapy can be given
•Teratoma/fibrosis only: observation only
TESTICULAR CANCER: NSGCT 305
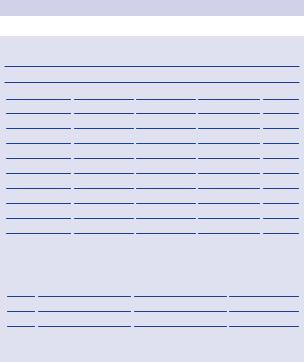
Table 6.18 Simplified stage grouping for testis cancer, including S stage
Simplified stage groupings in testis cancer
Stage 0 |
|
Tis |
N0 |
M0 |
S0 |
|
||
Stage IA |
|
T1 |
N0 |
M0 |
S0 |
|
||
Stage IB |
|
T2–4 |
N0 |
M0 |
S0 |
|
||
Stage IS |
|
T any |
N0 |
M0 |
S 1–3 |
|
||
Stage IIA |
T any |
N1 |
M0 |
S 0/1 |
|
|||
Stage IIB |
|
T any |
N2 |
M0 |
S 0/1 |
|
||
Stage IIC |
T any |
N3 |
M0 |
S 0/1 |
|
|||
Stage IIIA |
T any |
N any |
M 1a |
S 0/1 |
|
|||
Stage IIIB |
T any |
N any |
M 0/1a |
S2 |
|
|||
Stage IIIC |
T any |
N any |
M 0/1a |
S3 |
|
|||
|
|
T any |
N any |
M1b |
S any |
|
||
|
|
|
|
|||||
a, nonregional nodes or pulmonary metastasis; b, other distant metastasis. |
|
|||||||
|
|
|
|
|
|
|
|
|
|
LDH |
|
hCG mIU/mL |
|
AFP ng/mL |
|
||
|
|
|
|
|||||
|
|
|
|
|
|
|
|
|
S0 |
Normal |
|
Normal |
|
Normal |
|
||
S1 |
<1.5 ULN |
<5000 |
|
<1000 |
|
|
|
|
S2 |
1.6–10 ULN |
5100–50,000 |
|
1100–10,000 |
|
|||
S3 |
>10.1 ULN |
>50,100 |
|
>10,100 |
|
|
|
|
|
|
|
|
|
|
|
|
|
ULN, upper limit of normal.
•With no response to primary chemotherapy, consider salvage chemotherapy (ifosfamide, vinblastine, cisplatin), or salvage bone marrow transplant.
Chemotherapy
Regardless of histology, patients with advanced germ cell tumors (cIIB– cIII) and those with elevated tumor markers following radical orchiectomy (cIS) are treated initially with platinum-based chemotherapy based on IGCCCG risk stratification.
Good risk
Use BEP regimen every 21 days x3 cycles
•Bleomycin 30 U IV weekly
•Etoposide 100 mg/m2 IV x 5 days
•Cisplatin 20 mg/m2 IV x5 days
Or EP regimen every 21 day x4 cycles
•Etoposide 100 mg/m2 IV x5 days
•Cisplatin 20 mg/m2 IV x5 days

306 CHAPTER 6 Urological neoplasia
Intermediateor high-risk disease
Use 4 cycles BEP every 21 days (as above), or the following given every 21 days x 4 cycles:
•Etoposide 75 mg/m2 IV x 5 days
•Ifosfamide 1.2 g/m2 IV x 5 days
•Cisplatin 20 mg/m2 IV x 5 days
Chemotherapy complications
•Bleomycin: pulmonary toxicity causing pulmonary fibrosis that can be life threatening
•Cisplatin: nephrotoxicity, ototoxicity, peripheral neuropathy
•Etoposide (VP16): hematological toxicity, alopecia, vascular toxicity, metabolic syndrome
•Ifosfamide: hemorrhagic cystitis (can be reduced by the use of MESNA)
•Secondary malignancy: leukemias, lymphomas, skin malignancies
•Infertility: 50% will have normal sperm counts 2 years after chemotherapy, 25% will remain azoospermic (many patients with testicular cancer will have abnormal semen parameters before radical orchiectomy)
Surveillance and follow-up after treatment
Surveillance for low-risk disease requires the following. Patients who undergo definitive therapy can have less aggressive follow-up the first 2 years, but follow-up is also to 10 years. The risk of relapse is highest in the first 2 years.
•Year 1: monthly clinic visit with serum markers and chest X-ray, abdominal CT months 3, 6, 9, and 12
•Year 2: bi-monthly clinic visit with serum markers and chest X-ray, abdominal CT month 24
•Years 3, 4, and 5: 3-monthly clinic visit with serum markers and chest X-ray
•Annual clinic visit with serum markers and chest X-ray thereafter to 10 years
RPLND
RPLND is the gold-standard staging investigation following radical orchiectomy. In the United States, it is the preferred approach for patients at high risk for retroperitoneal relapse (predominant embryonal carcinoma, lymphovascular invasion, or extension into the tunica or scrotum) if serum tumor markers have normalized. In the UK, RPLND is used only to remove or debulk residual mass post-chemotherapy.
Retroperitoneal lymphadenopathy is usually the first and only evidence of extragonadal metastasis of teratoma. For low-stage disease, a modified nerve-sparing template is used.
Open RPLND is the standard, with laparoscopic techniques applied at some centers. It is a technically challenging procedure that requires significant expertise.